Showing posts with label 19th Century medicine. Show all posts

Thursday, August 30, 2018

Dr LEWIS SAYRE's 1862 TREATMENT FOR GUNSHOT WOUNDS


The Doctor's Bag

The blog about Medicine and Surgery in the Old West 

By Keith Souter aka CLAY MORE


Dr George Goodfellow, the surgeon to the gunfighters is famed as the doctor to treat your gunshot wound in the Old West. He developed his expertise during his practice in Tombstone and later on in Tucson in the 1880s and wrote a major paper on the subject in 1889. He was practising in the early days of antiseptic surgery and adopted Joseph Lister's methods of sterilizing instruments in carbolic acid and cleansing wounds with it. 


A hand-operated carbolic spray, such as Dr Goodfellow may have used


As western writers we often set out stories before the Lister era of aseptic surgery. I thought it might be useful to consider how earlier doctors might treat gunshot wounds, so here is a short paper from the American Medical Times of 1862, by Dr Lewis Sayre. He was a leading orthopaedic surgeon of the nineteenth century. 


Oakum as a Substitute for Lint, in Gunshot and other Suppurating Wounds

Dr LEWIS A. SAYRE recommends (Am Med Times, Aug 9, 1862) picked oakum as a substitute for lint, in all cases of suppurating wounds, particularly in connection with opened joints where the suppuration is excessive. The oakum, he says, is more of an absorbent than lint, and therefore fulfills one of the objects of dressing better, and another advantage is its cheapness.

"It is necessary," he says , "to place under the wound a piece of India-rubber cloth, or oiled muslin, for the sake f cleanliness; and in case of much inflammation, by simply wetting the oakum in cold water, and wrapping the oiled muslin around the limb, or wounded part, so as to exclude the air, you have at once the neatest and most comfortable poultice that can be applied to it. In gunshot wounds, which go through an through a limb, particularly if made with the 'Minié ball,' the whirl or screw of the ball entangles in its thread the muscular fibres and cellular tissue, and separates them from their attachments for a long distance from the real track of the ball itself.

"As the muscle and tegumentary tissues are more freely supplied with blood vessels than the the fat and cellular tissue, the consequence is that they begin to granulate more readily than those other tissues, and will thus often close up the wound, and prevent the free escape of pus, before those parts have perfectly healed, and thus lead to the formation of extensive secondary abscesses. I, therefore, in all cases where no blood vessels prevent it, pass an eyed probe through the wound and draw through it a few fibres of the oakum or tarred rope, which keeps it perfectly free, and the tar is a very excellent antiseptic, and removes all unpleasant odour.

"A few fresh fibres are twisted on the end of the seton *at every dressing and drawn into the wound, and the soiled piece cut off and removed with the dressings."


[* seton - a thread of gauze or other suture material threaded through tissue and used to keep a wound open.]


A three ring Minié ball, as invented by Claude-Etienne  Minié

Oakum
This was loose hemp or jute fiber, sometimes treated with tar, creosote, or asphalt, used chiefly for caulking seams in woodenships and packing pipe joints.


Oakum


In Victorian prisons and workhouses inmates were made to pick old ropes apart to produce oakum.


Tarred rope and oakum may be the answer in your stories of the really Old West

Hemp rope required tarring to prevent rot. So there you have it. 

If you are treating a gunshot in the 'really Old West,'  that is before aseptic surgery as advocated by Joseph Lister from 1865 (the date when he started using carbolic acid dressings and 1867 when he developed and started using his carbolic acid spray - picture above), then consider using  tarred rope strands as outlined above and wound dressing with oakum.


Dr Lewis A. Sayre (1820-1900)

To round off, you may be interested in a little background on this doctor. Lewis Albert Sayre, MD was a leading orthopaedic surgeon of the nineteenth century, who was a surgical innovator and a prolific medical writer. He was a founder of the Bellevue Hospital Medical College in 1861. This institution merged with University Medical College in New York in 1898 to become New York University School of Medicine. He was also a founding member of the American Medical Association, and was elected its president in 1880.


Dr Lewis Albert Sayre

He is most famous for being the first surgeon to operate to cure hip ankylosis (stiffness) and for his treatment of scoliosis, by suspending the patient to allow gravity to straighten the spine and then to put the body in a plaster cast. This treatment made a huge difference to many thousands of people. 


Although this may look alarming, the patient was actually in control and suspended herself prior to having the Plaster of Paris bandage applied to the torso to maintain the straight spinal position. He described this fully in his 1877 text Spinal disease and spinal curvature: their treatment by suspension and the use of the plaster of Paris bandage.

***


If you are interested in reading more about medicine and surgery in the frontier days, including the work of Doctor George Goodfellow, then you may find The Doctor's bag useful. It is a collection of my past blog posts, published by Sundown Press.


The novel about Dr George Goodfellow, the Tombstone surgeon to the gunfighters


The novel about Ned Buntline, the King of the Dime Novelists


Thursday, July 26, 2018

MAGGOT-RIDDEN WOUNDS


The Doctor's Bag

The blog about Medicine and Surgery in the Old West 

By Keith Souter aka CLAY MORE


The thought of a maggot-ridden wound makes most people cringe. Writers often pop such images into their tales for that very reason. The squirm factor can be effective in keeping the  reader reading. After all, a wound that has actual crawling maggots in it just seems so awful. It looks unclean and the reader may suppose that it is a bad sign.

The movies often have maggot-ridden scenes. Take Gladiator, for example. There is an early scene  with Maximus reaching to remove maggots from a gaping arm wound, only to be advised by his (soon to be) friend and fellow gladiator, Juba, to leave it alone. And indeed, the maggots clean the wound and it heals.

Aristotle's doctrine of spontaneous generation 
Maggots have had a bad press since antiquity. Aristotle proposed the theory of spontaneous generation, or abiogenesis. (a-bio, meaning 'without life', and genesis meaning 'origin of'). Essentially, it was a belief that living things grew from non-living matter. Maggots were seen to develop in rotting meat or in carcases. Similarly, the Egyptians had noted that frogs seemed to develop in the Nile mud after the annual inundation. 


Aristotle 384-322 BC

This theory survived for two thousand years until the Italian doctor and 'father of experimental biology,' Francesco Redi challenged the concept of abiogenesis. 


Francesco Redi (1626-1697)

He performed some rather elegant experiments on maggots and flies, which he published in 1688 as Esperienze Intorno alla Generazione degli Insetti (Experiments on the Generation of Insects). He concluded in this series of experiments  that flies laid eggs in decaying matter and that larvae (maggots) hatched from them and ultimately turned into adult flies. He did it using jars into which he put identical quantities of meat or fish. In one group the jars were covered with gauze, which let air in, but secluded entry to flies. The others were left open and exposed to flies. No maggots developed in the fly-excluded jars, but the others produced maggots, then a cocoon stage, from which adult flies emerged.


As you can see from the illustrations he used in his book he accurately described the life cycle of the fly, which undergoes a complete metamorphosis from egg to larva, to pupa, to imago or adult fly. 
Of course, Redi had to be careful about how he described this, because the church was so powerful and several men of science had paid dearly for declaring scientific theories that the church considered to be heresy. 

Biogenic generation
Accordingly, it was another two centuries before Louis Pasteur, a French scientist finally blew a hole in the theory of abiogenesis. 


Louis Pasteur (1822-1895)

To do this Pasteur prepared some  sterile nutrient broth and placed equal amounts in two flasks with swan shaped necks.  He broke the neck of one flask and left the other. The broth in the broken necked flask quickly became cloudy as micro-organisms grew in it. The other remained sterile, until he eventually broke the neck, when it also eventually became cloudy. The cloudiness was due to the presence of microorganisms. 


One of Pasteur's swan- neck flasks

The S shaped neck had prevented dust particles and microorganisms in the air from reaching the broth, until the neck was broken. 

Instead of the abiogenesis theory of spontaneous generation, we then had the theory of biogenic generation. 

Maggot-ridden wounds 
Although maggots have the association with decay, yet over the centuries it had been observed  that maggot-infested wounds  often did better than expected. 

The Mayans used to cover wounds in cloths soaked in animal blood and dried in the sun. When they started to pulsate, as maggots hatched and moved about, they believed that the wound would heal. Often it would. 

Aborigines in Australia used to actively put maggots into wounds to heal them. 

The french military surgeon, Ambroise Pare (1510-1590), one of the most notable surgeons of the Renaissance described the benefits he had seen in maggot-infested wounds. Similarly, the French surgeon, Baron Dominique-Jean Larry (1766-1842), observed that blue fly maggots seemed to remove necrotic or dead tissue from wounds and speeded up healing. 

During the Civil War maggot-ridden wounds were thought to be a bad sign of infection and soldiers were understandably distressed to see maggots in their wounds. Wars have always been times when medicine and surgery have been given opportunities to make advancements. This happened in a prison stockade in Chattanooga, where Confederate surgeons were not given supplies of bandages and dressings, or adequate amounts of chloroform (which was used to bathe wounds to clean them). Their  patients who had often developed gangrene were forced  to leave the wounds unbound and fly-infested, whereas Union surgeons de-maggoted their patients' wounds. Much to their astonishment  the maggot-ridden Confederate wounds cleared up far quicker and more effectively than the so-called cleaned and dressed wounds. Indeed, death rates were significantly lower in the Confederate patents. 

Dr William Williams Keen (1837-1932), observed that maggots certainly did not hamper recovery in many cases. He said that despite their revolting appearance, they were not detrimental to the healing process. After the war he studied in Paris and London and e would go on to become the first neurosurgeon in the USA.  


Dr William Williams Keen (1837-1932)

Doctors in the Great War also saw the surprising effects of maggot-ridden wounds. Dr William Stephenson Baer (1872-1931) was an American surgeon  serving with the American Expeditionary Force in France. In 1917 he treated two badly wounded  soldiers who had lain injured on the battlefield for seven days. Their wounds were totally maggot-ridden and at first he feared for their lives. Yet on examination and after clearing the maggots away, he found that the underlying tissues were clean, free of pus and that healing with granulation tissue was occurring. He said: " ...the wounds showed the most beautiful pink granulation tissue that one can imagine.” Both soldiers healed  swiftly and recovered completely.

Dr Baer went on to become the founding chairman of orthopaedics at John Hopkins University and a surgical innovator in both hip and spine surgery. He also followed up his work from the Great War and did research on thee use of maggot therapy (Maggot Debridement Therapy, or MDT) in the control of persistent wound and bone infection. In 1931 he wrote a paper, The Treatment of Chronic Osteomyelitis with the Maggot (Larva of the Blow Fly). It is considered one of the classic papers in surgery.

Maggot therapy
Not all maggot-ridden wounds will be clean, though. The problem is that the blow fly that lays the eggs is a vector, that means a carrier of disease. If it has contaminated mouthparts or feet, then it can cause the infection in a wound. If no infection is present, then the lava that hatch may indeed act as scavengers to eat up any necrotic tissue, kill organisms in the wound and absorb pus to allow healing to take place. 

Dr Baer actually grew larvae on a windowsill in the Baltimore Children's Hospital as he researched on the use of maggots in chronically infected wounds. Unfortunately two patients died from tetanus, which made him realise that the maggots had to be sterile. He managed to develop a technique of producing larvae in a sterile environment, after which the 1930s saw a huge rise in the use of maggot therapy. Lederle laboratories in New York  started to produce sterile maggots ands were able to supply hospitals.


Maggot therapy then fell into disuse when the sulpha drugs and then modern antibiotics were discovered and  became an essential part of modern medicine.  However, because of the developing worldwide problem with antibiotic resistance, chronic infections are again a problem and there has been a resurgence of interest and active research into the maggot and its abilities to clean wounds. 


***


If you are interested in reading more about medicine and surgery in the frontier days, including the work of Doctor George Goodfellow, then you may find The Doctor's bag useful. It is a collection of my blog posts, published by Sundown Press.


The novel about Dr George Goodfellow, the Tombstone surgeon to the gunfighters


The novel about Ned Buntline, the King of the Dime Novelists


Buy The Dime Novelist

Thursday, May 24, 2018

I THINK IT'S BUSTED, DOC!


The Doctor's Bag

The blog about Medicine and Surgery in the Old West 

By Keith Souter aka CLAY MORE


It is a dangerous business being a character in a western novel. You can get shot at, tossed off a horse, hurled through a saloon window or be pushed over a ravine. You have seen it on the movies, read it in the novels or written about it yourself. Any of them can have fatal consequences, but more often than not in this fictional world that we love so much the result is a broken bone somewhere. And then the Doc comes along just in time to hear that speculative diagnosis - "I think it's busted, Doc!"


Aiding a comrade by Frederic Remington

And of course, an examination reveals all, a splint is manufactured, a snort of whiskey or a dose or two of laudanum and "You'll be up and about in no time at all."

But in real life it is often more complex than that.


The birth of orthopaedics
We know that doctors have been setting bones since the days of the ancient Egyptians. We have surgical papyri outlining treatments and mummies have been found with splints made of bamboo, reeds, wood or bark, padded with linen.

The roman physician Galen (129-199 AD) treated gladiators and recorded his treatments in his medical and surgical encyclopedias. His treatments were used as the basis for treatments all the way up the the Renaissance.

The name orthopaedics was first used in 1741 in France, when Nicholas Andry, a professor of medicine at the University of Paris coined it from the Green words 'orthos,' meaning 'bone' and 'paideia' meaning 'rearing of children'. His book Orthopédie was about the prevention and correction of musculoskeletal deformities in children. There was a real need for this since there were many diseases that could cause problems like scoliosis (curvature of the spine), abnormalities in the growth of bones (e.g., tuberculosis), various infections (osteomyelitis), vitamin disorders (e.g. vitamin D deficiency causing rickets or bowed legs), and conditions that could cause paralysis, such as poliomyelitis.

So, the specialty of orthopaedics was originally all about treating children to prevent problems. The treatment of fractures became added along the way.

The frontispiece for his book showed a sapling supported by a staff. This has been taken as the logo of orthopaedic institutions and organizations across the world ever since.


In   Jean-Andre Venel established the first orthopaedic institute in 1781 for the treatment of children.

Splints and supports
As mentioned above, splints of various forms have been used from the times of antiquity. The purpose of them is simply to support the leg and prevent movement of the broken ends of the broken bone.

In medieval times surgeons knew that fractures bones had to be kept in place. One method of doing this was to soak bandages in horses' urine. As the bandage dried it would stiffen into a splint.

                  The Hodgen splint was invented in 1863 by John T Hodgen, a surgeon from St Louis. It was a suspension leg splint for fractures of the middle or lower femur.


Plaster of Paris casts
This was a fantastic addition to the surgeon's armamentarium of treatments. It was the invention of Antonius Mathijsen, a Dutch military surgeon in 1851. Essentially, a continuous bandage is wound round and round the limb then soaked in Plaster of Paris. It is called this because it was first used extensively in Paris in medicine and in building.


Essentially, it is made from gypsum, which is heated to produce anhydrous calcium sulphate. When water is added to this it forms gypsum again and hardens.  Hardening takes place very quickly, but it has to dry out. The larger the cast, the longer it takes. An arm cast will dry out in 3-6 hours and a leg cast may take up to 6 hours.Yet full drying may not be complete for 72 hours.
                             
                  Nikolai Pirogov is credited as the first surgeon to use them to treat casualties in the Crimean War in the1850s, so of course, Dr Logan Munro was aware of the method and would use it in his practice in Wolf Creek!


Diagnosis of fractures
Nowadays we are very dependent on x-rays, but in the old West there was no such thing. William Roentgen discovered them in 1895. Only a year later, Dr John Hall-Edwards in Birmingham, England started to use the so-called X-rays in medical diagnosis.

In the Old West doctors relied on physical examination to diagnose fractures. Then, and now fractures would be divided into two broad types:

Closed or simple fractures - when the skin is intact.
       
Open or compound fractures - when the broken bone protrudes through the skin.

The type of fracture can vary immensely. We talk about a 'clean break' meaning a simple transverse fracture. But it can also be oblique, as can happen with a torsion or twisting  injury. Or it can be comminuted, meaning fragmented. It can be complicated by causing blood vessel or nerve damage. And it can be a 'greenstick' (as happens in youngsters, when a bone gets bent and only partially fractures).


The principles of treatment of fractures was relatively simple then. If moving the part of the body distal to (furthest away from the site of the pain) caused extreme pain or if  grating could be felt, then a fracture would be diagnosed. 

The bone had to be set. That is, the limb had to be stretched in order to make sure it was the same length as the other. This would give the best chance to get the two broken ends in position against one another to allow healing to take place.

Without the use of x-rays it is very likely that all manner of injuries would end up being diagnosed as a fracture. The treatment would involve immobilizing the part and hopefully, the injured part would just 'knit together' and be whole again after a few weeks. Remember, that nature actually does the healing, not the doctor, surgeon or nurse. All that they do is create the best circumstances for nature to do its job.

And of course if the 'broken bone' healed up all right, it would bring nothing but kudos to the doctor, whether it actually had been a fracture or not.


Bone healing
What actually happens when the bone ends are back in opposition is that a large haematoma, or blood clot forms around the ends. This is rather like jelly. After a few days blood vessels grow into it and cells called phagocytes start digesting any debris and tissue that won't heal. Then other cells called fibroblasts start to lay down collagen, that forms a framework around the bone ends. This secures the  one ends and new bone is laid down. As a rule of thumb, most bones will have knitted in about 6 weeks.

Some fractures worth knowing about
There are lots of different fractures, many of which are named after the doctors or surgeons who first described them. Some of the ones which our western doctors would have known about are as follows:

Colles fracture
A fracture of the distal radius one inch (2.5 cm) above the wrist. It was described by Abraham Colles an Irish professor of anatomy in 1814. It is sustained by falling on the outstretched hand as when you try to break your fall. The problem is that the broken bone gets displaced and causes a dinner-form abnormality if it is not replaced in posit and immobilized. It takes 4- 6 weeks to heal. 

Smith's fracture
By contrast, a Smith's fracture, also known as a Groyland-Smith fracture is a 'reverse' Colles fracture. It was described by the Irish orthopaedic surgeon Robert Smith in his 1847 book,  Treatise on Fractures in the Vicinity of Joints, and on certain forms of Accidents and Congenital Dislocations.  

 It is a fracture  of the distal (bottommost) part of the radius, caused by a blow to the back of the forearm, or a fall on the flex wrist. 

Thus, a Colles fracture is an extension injury and the Smith's fracture is a flexion injury. 


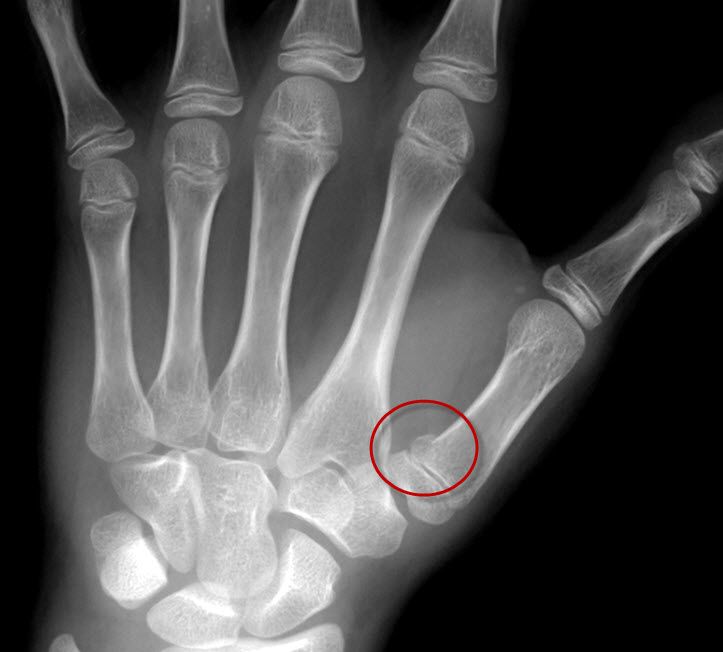
Bennett's fracture 
This is one that could occur in saloon brawls, or whenever a really hard surface was punched. If you swing at someone and they duck, causing you to punch the wall, you may end up with a Bennett's fracture.
Bennett's fracture

It can also occur if someone punches someone else's skull! It is a fracture of the first metacarpal, the big bone at the base of the thumb. It is also common in people who have never learned how to punch correctly - which is most people! It was described by Edward Hallaran Bennett, professor of surgery at Trinity College Dublin in Ireland in 1882. It needs immobilization of for 4-6 weeks.

Scaphoid fracture
This is not named after anyone, but is the name of one of the bones of the wrist. It also occurs when you try to break your fall. It causes pain in the 'anatomical snuffbox.'  This is an area at the base of the thumb. It is called this because in days of yore when folk took snuff, they placed a pinch in the little depression on the back of the wrist formed when you elevate the thumb perpendicular to the hand. 

The anatomical snuffbox outlined

The problem with this fracture is that the scaphoid has a variable blood supply and in many people the blood supply comes distally. That is, blood vessels do a U-turn to supply the bone from its far end. If they do not also have a blood supply going directly into the base of the bone (that is, from the top and bottom) then non-union of the bone can occur and the piece without the blood supply can die.

Monteggia fracture
This is a fracture of the proximal third of the ulna (the larger bone in the forearm) with dislocation of the head of the radius (the smaller bone). It was named after Giovanni Monteggi, (1762-1815) an Italian professor of anatomy and surgery. It occurs with a fall and a twist. 

Monteggia fracture, by Jane Agnes

It is a difficult one to treat because the breaks and the two bones are hard to get in the right positions.  Nowadays it may necessitate operation.

Clavicle fracture
The collar bone is commonly injured in contact sports and fights. A direct blow to the upper chest can  fracture it, most usually at the junction between the middle and outer thirds. They heal up very well generally. We used to use figure of eight bandages and a sling, but really they generally just heal without any intervention.


Fracture of neck of femur
The femur is the thighbone. The two main parts are the neck of the femur, where it forms the hip joint and the shaft, the main part of the thigh.  This is the sort of fracture that happens in older people who may have osteoporosis, or thinning of the bone. This is nowadays treated by internal reduction and fixation. It is probably not going to occur to your hero or heroine in the western novel, but could to another character. It classically causes a great deal of pain after a fall or twist, and the leg will show external rotation due to the weight of the limb.


Fracture of the shaft of the femur
This can occur with any large trauma, either directly from a blow or from a fall. Depending upon which part of the shaft is affected the muscles will move the two parts ion different directions. The first aid treatment would be to strap the two legs together, so that the good leg acts as a splint.

Skull fracture
The big thing here is the possibility of a hemorrhage inside the skull or into the brain. In terms of the novel, the big question would be whether to trephine or not. That is, whether to make a hole in the skull to release blood.

This just happens to be one of the questions that Doc Logan Munro is forced to consider in Wolf Creek 8: Night of the Assassins. But you will find no spoilers here!

***

If you are interested in reading more about medicine and surgery in the frontier days, then you may find The Doctor's bag useful. It is a collection of my blog posts, published by Sundown Press.


The novel about Dr George Goodfellow, the Tombstone surgeon to the gunfighters


The novel about Ned Buntline, the King of the Dime Novelists

The Dime Novelist